





Modern medicine is built on precision: exact dosages, targeted therapies, and highly specialized surgical interventions. Yet, this entire ecosystem relies on a single, astonishingly fragile data point: accurately identifying the patient.
Patient identification—the essential process of inextricably linking an individual to their specific medical records and treatment plan—is the foundational protocol of healthcare. When this initial verification fails, the error cascades through every department, transforming otherwise flawless clinical execution into a critical safety event. Today, patient misidentification remains one of the most persistent, dangerous, and expensive vulnerabilities in the medical system. Indeed, 86% of healthcare professionals report having witnessed a medical error caused directly by patient misidentification [1]. Unsurprisingly, improving patient identification accuracy remains prioritized as Goal 1 of The Joint Commission's National Patient Safety Goals [2].
The systemic scope of clinical misidentification
Misidentification is rarely an issue of individual negligence but a procedural problem. The ECRI Institute routinely ranks patient misidentification among its top safety concerns, noting that errors originate across the entire continuum of care— from fragmented registration databases down to the bedside [3]. As detailed in Figure 1, more than half of these failures concentrate downstream during diagnostic procedures (36.5%) and direct treatment (22.1%), where a mismatched record translates immediately into clinical harm [3]. The stakes of this vulnerability are absolute. Overall medical errors represent the third leading cause of death in the U.S., responsible for between 195,000 and 400,000 fatalities annually—over 1,000 deaths a day [4,5]. Patient identity mix-ups directly fuel this crisis, compromising care across 10 of the 17 core Patient Safety Indicators tracked by federal health authorities—including improper blood transfusions, diagnostic delays, and wrong-site surgeries [3].
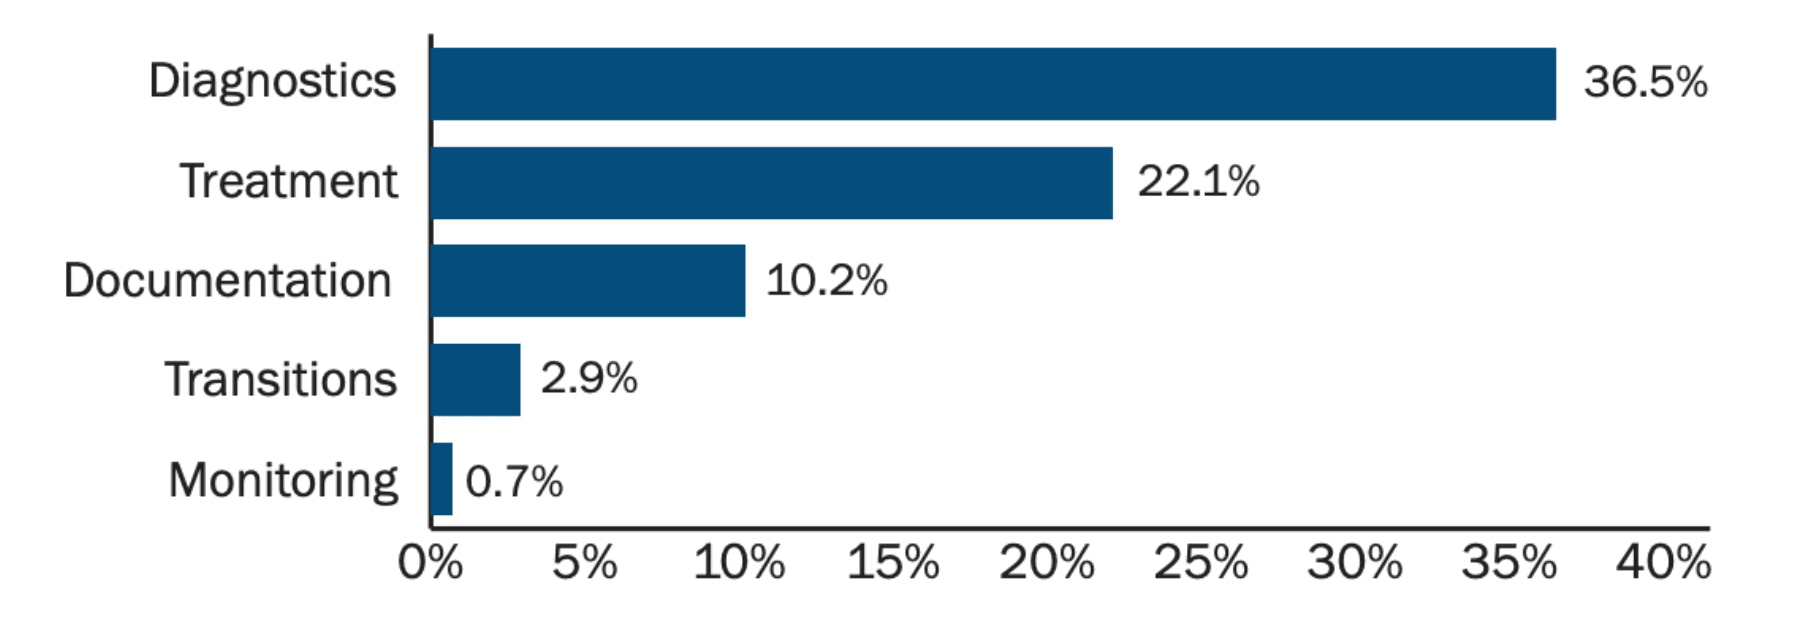
The clinical damage can also be a consequence of non-direct patient interactions. In clinical laboratory specimens, misidentification occurs at approximately a 1% rate [6]; in transfusion medicine, the frequency is around 0.01-0.1%, with up to 10-20% of these errors translating into patient harm [7]. That means patients being treated for conditions they don't have, or missing early interventions for those they do. Step into high-acuity environments like the ICU or operating room, and the stakes climb dramatically.
The operational and financial impact of misidentification
The consequences of clinical misidentification also choke daily hospital operations. Nurses and registrars lose nearly 30 minutes every shift resolving identity mismatches, hunting down missing charts, and verifying demographic fields [1]. When a patient's historical record remains hidden or fragmented, clinicians cannot afford to wait. To protect the patient, they re-order blood panels, rerun imaging scans, and perform duplicate diagnostic tests—wasting critical time and running up unnecessary expenses.
When a mix-up slips through and triggers a severe adverse event, the hospital pays a heavy operational price. Research from the Agency for Healthcare Research and Quality (AHRQ) shows that major medical errors extend a patient's stay by 4.5 to 7.2 days on average [8]. Those extra days stall emergency room transfers, bottleneck bed turnover, and consume resources that cannot be billed.
In billing departments, demographic mismatches create an immediate financial leak. Roughly 33% of all denied insurance claims stem from basic demographic mismatches - a misspelt last name, a wrong date of birth, or an outdated policy number [9]. Appeals require hours of manual rework by billing staff, and many claims are written off entirely. For an average hospital, this friction costs $1.2 million a year in lost revenue and administrative overhead [1].
The gold standard: why barcodes and wristbands keep failing
To understand why this keeps happening despite mandatory barcode scanners and wristband policies, you have to look at how care actually gets delivered under pressure. Identification errors do not solely happen due to lack of training but due to high-friction and high-interruption environments. At the bedside, standard patient safety protocols require active identification—prompting the patient to state their full name and date of birth.
Moreover, when high-volume workflows lead clinicians to rely on passive leading questions ('Are you Mr. Davis?'), confirmation bias replaces rigorous verification, creating an immediate point of failure.
More importantly, physical tokens fail precisely when patients are most vulnerable. In trauma bays, surgical wards, neonatal units, or memory care wards, self-reporting isn't even an option. Wristbands get cut off for line placements, soiled by fluids, or misplaced during emergency transfers.
Bedside misidentification rarely starts at the bedside. More often, it is fed by a quiet crisis in the hospital's back-end database: record duplication.
When a patient ends up with two or more profiles in a Master Patient Index (MPI), their clinical history gets split. A doctor treating them in the ER might only see half the picture—missing critical allergy alerts, recent lab work, or active prescriptions stranded in a duplicate file. Indeed, around 4% of cases involving confirmed duplicate records lead to the clinical care being negatively affected [10].
This problem explodes during health system mergers. Combining disparate Electronic Health Record (EHR) systems pushes duplicate rates in large networks as high as 15% to 16% [10]. And these duplicates aren't obvious. More than half of duplicate record pairs stem from subtle gaps—a missing middle initial, a misspelt name, or a default placeholder in the Social Security field [11].
Worse still is the 'overlay': when two distinct patients are mistakenly merged into a single file. At that point, clinicians aren't just working with incomplete data—they are treating one patient based on another person's medical history
Recognizing that human vigilance and local software tweaks are no longer enough, federal regulators are taking aim at the root cause: unstandardized demographic data. Through initiatives spearheaded by the Office of the National Coordinator for Health IT (ONC) [12], the healthcare industry is shifting toward standardized patient-matching protocols.
National standards set a necessary baseline, but a policy rule cannot stop a mix-up in the middle of a chaotic shift. Clean data in a database is only half the battle; hospitals still need reliable technology that works where care actually happens—at the bedside. As health networks expand, protecting both patients and hospital budgets comes down to a simple requirement: tools that ensure, without added friction, that every patient receives the exact treatment intended for them.
References
- Ponemon Institute & Imprivata. (2016). National Patient Misidentification Report. Imprivata. https://security.imprivata.com/rs/413-FZZ-310/images/PS-AR-2016-National-Patient-Misidentification-Report-1216.pdf
- The Joint Commission. (2023). National Patient Safety Goals®. Goal 1: Improve the accuracy of patient identification. Available at: https://www.jointcommission.org/standards/national-patient-safety-goals/
- ECRI Institute PSO. (2016). Deep Dive: Patient Identification – Executive Summary. ECRI Institute.
- Healthcare Innovation. (2016). Johns Hopkins Research Finds Medical Errors Third Leading Cause of Death in U.S. Available at: https://www.hcinnovationgroup.com/policy-value-based-care/news/13026728/johns-hopkins-research-finds-medical-errors-third-leading-cause-of-death-in-us
- Makary, M. A., & Daniel, M. (2016). Medical error—the third leading cause of death in the US. BMJ, 353, i2139. https://doi.org/10.1136/bmj.i2139
- Plebani M, Sciacovelli L, Aita A, Chiozza ML. Harmonization of pre-analytical quality indicators. Biochem Med (Zagreb). 2014 Feb 15;24(1):105-13. doi: 10.11613/BM.2014.012. PMID: 24627719; PMCID: PMC3936970.
- Lippi, G., Mattiuzzi, C., Bovo, C., & Favaloro, E. J. (2017). Managing the patient identification crisis in healthcare and laboratory medicine. Clinical Biochemistry, 50(10–11), 562–567. https://doi.org/10.1016/j.clinbiochem.2017.02.004 ,
- Zhan C, Miller MR. Excess length of stay, charges, and mortality attributable to medical injuries during hospitalization. JAMA. 2003 Oct 8;290(14):1868-74. doi: 10.1001/jama.290.14.1868. PMID: 14532315.
- Black Book Market Research. (2018). Master Patient Index & Patient Identification: Enterprise Solutions and Revenue Cycle Impact Survey. Black Book Research. https://www.blackbookmarketresearch.com/
- Hillestad, R., Bigelow, J. H., Chaudhry, B., Dreyer, P., Greenberg, M. D., Meili, R. C., Ridgely, M. S., Rothenberg, J., & Taylor, R. (2008). Identity Crisis: An Examination of the Costs and Benefits of a Unique Patient Identifier for the U.S. Health Care System. RAND Corporation. https://www.rand.org/pubs/monographs/MG753.html
- Just BH, Marc D, Munns M, Sandefer R. Why Patient Matching Is a Challenge: Research on Master Patient Index (MPI) Data Discrepancies in Key Identifying Fields. Perspect Health Inf Manag. 2016 Apr 1;13(Spring):1e. PMID: 27134610; PMCID: PMC4832129.
- Stevens, L. (2013, September 11). ONC launches patient matching initiative. Health IT Buzz. Office of the National Coordinator for Health Information Technology. https://www.healthit.gov/buzz-blog/health-innovation/onc-launches-patient-matching-initiative/
